Showing posts with label Super Bugs. Show all posts

Tuesday, March 12, 2013

Losing Touch in the Era of Superbugs? (from pubMed)


Ann Fam Med. 2010 September; 8(5): 461–463.
PMCID: PMC2939423

Losing Touch in the Era of Superbugs?

Abstract

Nosocomial infections are increasingly multidrug resistant and at times more virulent. As such, they pose real threats to patients and clinicians. In this essay the author discusses his own methacillin-resistant staphylococcus infection and how it has affected his work in the hospital. In so doing, he reflects on the value of touch in the doctor-patient relationship. In particular, he discusses how gloves serve as a barrier to infection but also create a small distance between the doctors and their patients. The implications of contact precautions must be considered as we reflect on balancing patient-centered care with infection control.
Keywords: Physician-patient relations, trust, MRSA
The plastic gloves I put on as I enter the patient’s room are 2 sizes too small. They pull at the hairs on the back of my hand. Locating them, putting them on, disposing of them, all add to the sense of busyness that pervades my days as a hospitalist. Then, of course, there is the physical separation that the gloves create—something that gives me pause.
The room I enter is that of Mr Jones, a 54-year-old man with poorly controlled diabetes and a 1-cm ulcer on his left great toe. I explain, in what has become an extended part of my introduction of myself, that I wear gloves when I examine all patients to curb the spread of germs. As is typical, I hear no hint of disappointment from him, but for me, there inevitably is a slight sense of loss as I proceed with my examination.
Mr Jones leads a life that appears to have little intimacy. He lives alone in a notoriously rundown residential hotel where he keeps to himself to avoid the violence that plagues his neighborhood. Upon admission, he detailed to me with frustration the difficulties he has had getting care. Last week when he called a county clinic about his blood glucose levels of 350 mg/dL, he was told to follow-up in 4 weeks. Getting Mr Jones’s glucose levels down and treating his foot infection won’t be enormously difficult, but in the long run what he needs to improve his health is to feel invested in his relationship with the health care system. Faith in one doctor might provide him with the perseverance he needs to connect with another doctor in the haphazard world of safety-net health care. Any distancing could jeopardize the building of trust essential in a good doctor-patient relationship. I am afraid he might experience my use of gloves as a desire to keep an emotional in addition to a physical distance.
Leaving Mr Jones’ room, I hear cries in Cantonese from another patient of mine, Ms Chua. She is 89 years old with advanced dementia, and she had been sent from the nursing home because of increasing agitation and a fever. Twenty-four hours into her admission her fever has abated, but she has remained agitated. I enter the room, speak in soothing tones, and gently stroke her forehead. The smooth glide of skin on skin is missing. My hands, sweaty in the vinyl gloves, move less fluidly than they otherwise would. There is a loss of what could have been a brief soothing moment for us both. Even in her delirium, I imagine she can tell this is an institutional comforting because of the feel and smell of plastic.
My sense of loss commingles with ongoing ruminations about the consequences of not having started to wear gloves sooner. I have always thought I was a good hand-washer, but if I had been wearing gloves routinely last year, perhaps my daughter and I would not have been hospitalized with methicillin-resistant Staphylococcus aureus (MRSA).
Last year Josephine, my 10-year-old daughter, scraped her knee on the playground; for 2 weeks it was sore, and then suddenly it was red and warm. I started her on trimethoprim-sulfamethoxazole; even so, she had a temperature of 102 degrees the next day, so we brought her to the hospital, where she stayed for 3 days getting antibiotics.
A month after that, I developed pain in my arm without any redness or swelling. In an effort not to doctor myself, I saw an orthopedist who thought it was a biceps tear and put me in a splint. Two days later, I returned from work in worse pain and exhausted. After I collapsed on the couch, Josephine took off my splint and made the diagnosis. “Daddy” she said, “you have the same infection I had. You need to go to the hospital.”
I had developed a deep tissue infection without a clear port of entry and, as were my daughter’s, my wound cultures were positive for MRSA. During my hospitalization I was happy to be handled with gloved hands. I needed a couple of surgeries to ensure the wound was clean then went home on intravenous vancomycin
My wife, an epidemiologist, asked about treating our other young children and sterilizing the environment after our daughter’s hospitalization. I explained that, despite my urge to treat the whole family with mupirocin and topical antibacterial soap, I was following the recommendations of the pediatric infectious disease guy I had cornered during my daughter’s hospital stay. “MRSA is pandemic.” he said, “There is no reason to treat it differently than other skin infections.”
When I was hospitalized, my wife, at home with our 3 young children, was immediately on the telephone with her physician colleagues and getting informal consultations from national authorities on staphylococcus. She also got a good dose of MRSA horror stories–including tales of loss of limbs, life, and recurrent infections in colonized households. When I got home, she and the kids were on a 2-drug regimen and getting daily chlorhexidine baths. Never was a house so clean, but with an invisible threat, it remained hard to feel entirely safe.
My return to work after my illness was more difficult than I like to admit. I reflected on my training in family medicine at San Francisco General Hospital. I learned to focus on the whole patient rather than their specific ailments. Sometimes 50% of patients in my care of had human immunodeficiency virus (HIV). Advanced HIV brought with it other infectious concerns, such as tuberculosis, but I went about my work fearlessly out of professional duty and solidarity with my patients. I remember feeling self-righteous at what I believed were overly vigilant and stigmatizing precautions being taken by other health professionals. I hoped these memories would bolster my determination to “lay on the hands” again. But the hospital wards that had been so familiar now seemed like uncontrollable pools of pathogens the rest of the staff managed to blithely ignore. In every patient I saw threats to my family and myself. In addition to wearing gloves and now a white coat as well, I washed my hands, stethoscope, pagers, and pens obsessively. This behavior has improved with time, but I still feel that I am putting my family at risk every day I go to work. Given the trajectory of drug resistance, it is hard to imagine these thoughts will ever entirely go away—nor do I honestly think they should.
I understand objectively that I do not need to wear gloves with all my patients, but for a great number of patients, all clinicians must take considerable precautions to prevent the spread of infection. Guidelines support the use of alcohol-based foam products rather than gloves except when multidrug-resistant pathogens are confirmed, but given the increasing rates and virulence of these organisms, I am not convinced such measures will continue to be enough to protect our patients.1,2 I know, however, another important reason I now wear gloves is out of fear for my family and me.
Yet I see touch as a communication tool. For me, touch is particularly important when trying to bridge large socioeconomic and cultural gaps. A hand on the shoulder or the knee or a thoughtful physical examination, I believe, can make a patient understand at a deep nonverbal level you are there for them. I work hard to demonstrate concern for my patients with tone of voice, facial expressions, and body language, yet I feel I am losing some connectedness without skin-to-skin contact.
At the end of the day I go back to see Mr Jones to relay to him some good news. His bone scan suggests he does not have osteomyelitis. With the news of his scan, Mr Jones smiles for the first time in the 3 days I’ve been seeing him. “I guess I‘ll be getting out of here in a couple of days then. You’ll follow me in your office, won’t ya doc?”
I put a gloved hand on his shoulder and say “I don’t see patients outside of the hospital, but I’ll send you to see my buddy at the downtown clinic; she’ll do you right.”
“That’s what I need, doc. Someone I can count on.”
“You’re a good man, Mr Jones,” I say as I prepare to leave the room. “It’s going to take hard work to get yourself healthy again, but I know you can do it.”
As I toss my gloves in the trash and head out of the room, I realize that the people most in need of touch—those who have the greatest need to connect with a fellow human being, those I did not hesitate to touch without gloves in the past—have now become those I am most hesitant to touch without them. I am working up to not wearing gloves all the time. I hope that as I do become more relaxed, I won’t stop paying attention to nonverbal communication or the psychological consequences of illness, and my patients don’t end up feeling dehumanized by their hospitalization. We must not “lose touch” with what it is to provide patient-centered care as we navigate the increasingly complicated world of medicine in the 21st century.

Notes

Conflicts of interest: The author claims no financial or professional conflicts of interest.

REFERENCES

1. Siegel JD, Rhinehart E, Jackson M, Chiarello L, the Healthcare Infection Control Practices Advisory Committee. Management of Multidrug-resistant Organisms in Healthcare Setting. Washington, DC: Centers for Disease Control; 2006.
2. Hand hygiene in healthcare settings. Centers for Disease Control and Prevention Web site.http://www.cdc.gov/HandHygiene/index.html. Accessed Mar 3, 2009. Updated May 5, 2010.

Articles from Annals of Family Medicine are provided here courtesy of American Academy of Family Physicians

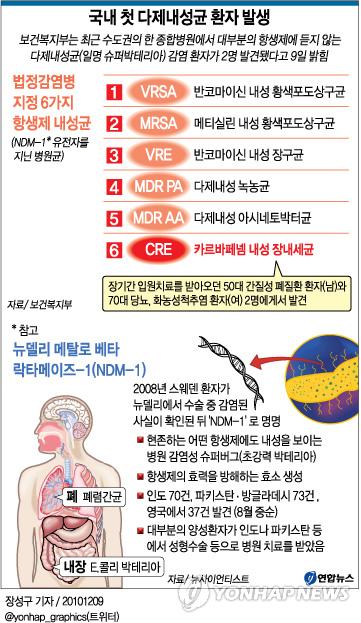
법정감염병 지정 6가지 항생제 내성균

법정감염병 지정 6가지 항생제 내성균(MDM-1 유전자를 지닌 병원균)


Fighting Super Bugs: Overcoming Antibiotic Resistance


Fighting Super Bugs: Overcoming Antibiotic Resistance


게시 시간: 2012. 12. 20.
(Visit: http://www.uctv.tv/) Paul Jackson, Division Leader of the Biosciences and Biotechnology Division at Lawrence Livermore National Lab, presents a brief history of antibiotic use and discusses the medical and public policy factors that are, in part, responsible for increased antibiotic resistance in pathogenic microbes. He and biology teacher Frankie Tate then introduce a new generation of antimicrobial compounds that are derived from the bacteria's own genes that may be clinically useful to treat infections caused by antibiotic resistant pathogens.

Series: "Field Trip at the Lab: Science on Saturday" [12/2012] [Science] [Show ID: 24518]
  • 카테고리

  • 라이선스

    표준 YouTube 라이센스

Rise of the Superbug - Antibiotic-Resistant Bacteria: Dr. Karl Klose at TEDx


Rise of the Superbug - Antibiotic-Resistant Bacteria: Dr. Karl Klose at TEDx


게시 시간: 2013. 01. 26.
Please note: Due to a power outage at the event, there is a gap in the middle section of this talk. We do not have capture of that section of the talk, but wanted to make as much of Dr. Klose's talk available as possible.

As founder and director of the South Texas Center for Emerging Infectious Diseases, with 19 infectious disease laboratories, Dr. Klose's research focuses on understanding bacterial pathogenesis in order to develop effective vaccines and therapeutics.

For more information on Klose: http://bio.utsa.edu/faculty-staff/dr....

Overview: The Superbug does exist. Dr. Klose offers profiles of bacteria and their sinister ways of evolving into antibiotic-resistant menaces. A cleverly designed slideshow accompanies Dr. Klose. 'No more meat treated with antibiotics' might be your take-away mantra.

About TEDx, x = independently organized event
In the spirit of ideas worth spreading, TEDx is a program of local, self-organized events that bring people together to share a TED-like experience. At a TEDx event, TEDTalks video and live speakers combine to spark deep discussion and connection in a small group. These local, self-organized events are branded TEDx, where x = independently organized TED event. The TED Conference provides general guidance for the TEDx program, but individual TEDx events are self-organized (subject to certain rules and regulations).

Video Opener by Rod Guajardo foursandyfeet.com. Music: MUSICXXX Kevin MacLeod (incompetech.com) Licensed under Creative Commons Attribution 3.0.

Help us caption and translate this video on Amara.org:http://www.amara.org/en/v/BWQo/

MRSA 란?


source: http://www.gunung.co.kr/nursingdata/1993


MRSA 란? 

: Staphyloccus aureus 는 그람양성구균으로 이중 페니실린 항생제인 Methicillin 에 내성을 보이는 균을 MRSA( Methicillin-Resistant Staphyloccus aureus)라 부릅니다. 
MRSA 감염발생시 다른 환자로부터 전파가 쉬워 집단감염으로의 발생 소지 가 많습니다.현재 치료제로 쓰이는 것은 Vancomycin이며, 이의 남용은 또다른 다 약제 내성균주의 출현을 초래할 수 있습니다. 

전파경로 

1) 접촉전파-MRSA균에 감염된 환자나 오염된 물체를 만진 후 손을 씻지 않거나 다른 환자와 접촉할 경우 전파되는 경우가 대부분입니다. 

2) 공기전파-환자의 기침이나 인공호흡기의 호기 배출기 또는 상처 치료시 공기 중으로 전파될 수 있으나 확실하지는 않습니다. 

관리지침 

1) 손씻기-MRSA감염 또는 보균환자와 접촉후 일시적인 보균상태가 될 수 있습니 다. 손씻기는 전파를 차단하는 가장 중요한 방법으로 매 환자와 접촉한 후 반드시 손을 씻어야 합니다. 

2) 장갑 - 감염의 우려가 있는 체액이나 물품과 접촉시 장갑을 착용해야 합니다. 같은 환자일 경우에도 다른 부위를 접촉하게 되면 장갑을 교환합니다. 

3) 가운 - 체액이 튈 우려가 있다면 착용해야 합니다. 

4) 마스크 - 호흡기 분비물에서 균이 분리되는 경우라면 출입시 마스크를 착용 합니다. 

5) 의료물품은 환자 자신의 것을 준비합니다.그리고 다른 환자에게 사용하기 전에는 반드시 소독합니다. 

6) 격리 - 호흡기 분비물에서 균이 배출된다면 1인실에 격리하는 것이 좋습니다. 

기타 다른 부위에서 분리되는 경우에는 1인실까지는 아니나 같은 환자끼리 같은 장소에 집중관리 하는 것이 좋습니다.

Pan-resistant?? The rise of Acinetobacter

source: http://www.superbugtheblog.com/search/label/Acinetobacter

see also:  The Fatal Menace of MRSA the SUPER BUG


17 JUNE 2010

Pan-resistant?? The rise of Acinetobacter

This is an addition for archival purposes of a post that originally appeared at Scienceblogs.


A set of papers published this month in two journals provide an unsettling glimpse into the rocketing incidence and complex epidemiology of one really scary pathogen,Acinetobacter baumanii.

In the all-star annals of resistant bugs, A. baumanii is an underappreciated player. If people -- other than, you know, disease geeks -- recognize it, that is because it's become known in the past few years for its propensity to attack wounded veterans shipped to military hospitals from Iraq and Afghanistan, earning it the nickname "Iraqibacter." (Important note: Steve Silberman of Wired magazine took an early look at this phenomenon in 2007, in a great story that analyzed the epidemiology of Iraqibacter to show that military infection control, not the environment of Iraq, was to blame for the bug's rapid emergence.) A. baumanii is a nasty bug, causing not just wound infections but pneumonia, urinary tract infections, meningitis and bacteremia. Even more nasty, it collects resistance factors like baseball cards, and is commonly resistant to at least 4 antibiotic classes. The most resistant strains are susceptible only to the so-toxic-we-put-it-back-on-the-shelf-decades-ago antibiotic colistin.

This is a particular concern because A. baumanii is a Gram-negative bacterium -- and while the drug-development pipeline for Gram-positives such as MRSA has slowed practically to a trickle, the one for Gram-negatives has dripped itself dry. As the Infectious Diseases Society of America and Jerome Groopman of the New Yorker highlighted back in 2008, drugs for Gram-negatives are barely on the agenda for the few companies still conducting antibiotic development.

So, the first piece of bad news. In Infection Control and Hospital Epidemiology (ICHE), a team from Brooke Army Medical Center in San Antonio take a look at their incidence of resistant Ab and find it exploding. Between 2001 and 2008, the percentage of A. baumanii isolates that were resistant to at least 3 classes of drugs went from 4% to 55%; of all the isolates, 17% (127) were resistant to at least 4 drug classes, and one was resistant to, well, everything.

How does A. baumanii spread so fast? A second paper in ICHE suggests a reason: The bug seems to do a better job than other resistant pathogens of contaminating the gear and hands of health care workers. A study done at University of Maryland found that when health care workers took care of A. baumanii patients, they ended up with contaminated gowns and gloves 39% of the time, and with contaminated hands (after glove removal) 4.5% of the time. Those are higher rates than for MRSA (18.5% of encounters) or VRE (8.5%).

A review article in Clinical Infectious Diseases reminds us why we should care about this: It examines the drugs to which some strains of A. baumanii are still susceptible, and finds all of them significantly toxic to different organs (kidneys, liver, pancreas, red blood cells, ) at the doses necessary to wipe out the bug.

Which is all troubling by itself. But a paper and editorial also appearing in Clinical Infectious Diseases make the case for A. baumanii as a bigger threat than has been understood. The bug's recent epidemiology has shown a distinct split, between the highly resistant forms affecting veterans, most of them being treated in the military evacuation chain, and less-resistant forms affecting civilians in hospitals (including in the Brooks data in the paper above). The severe wounds, aggressive treatment and rapid multiple transfers of personnel in the military system inadvertently created an environment that not only put A. baumanii under great selective pressure, but also spread it with startling efficiency.

The paper, reporting data from 4 community hospitals near Detroit, shows that the civilian medical system -- that would be the one that most of us live in -- has duplicated that churning as well. Between 2003 and 2008, all A. baumanii in their network increased 25%. A. baumanii resistant to the first 2 front-line drugs went from 2% to 33% of isolates. And "pan-resistant" A. baumanii -- resistant to all 8 drugs available for it, an essentially untreatable strain -- went from nonexistent to 14% of all the isolates that network found.

The effect on the patients was dramatic, of course: The more resistant their strains were, the more likely they were to never go home from the hospital, but (if they did not die there) to be discharged instead to a nursing home, long-term acute care facility, or hospice. But the larger point is that they carried that multiply-resistant strain with them, distributing it throughout the region: Patients came to those 4 hospitals, carrying A. baumanii, from 17 different nursing homes; from the 4 hospitals, carrying A. baumanii, they were transferred out to 28 different nursing homes.

This is a smart analysis, and devastating in its implications. American hospitals do a debatable job right now of handling infection control -- but overwhelmingly, they are handling infection control as individual institutions, not as competitors in a local market, and certainly not as members of a geographic region. Yet this data demonstrates clearly that cooperation between hospitals and other healthcare institutions -- most of which don't have hospitals' infection-control budgets or personnel -- is going to be essential if we want to put the brakes on Acinetobacter before it soars in the civilian medical system in the same way it did in the military one.

05 FEBRUARY 2010

Bad news in the President's budget request

It's been a few days since the rollout of the White House's proposed 2011 budget request, time enough for people to dig deep into the minutiae and figure out what that massive document really says. The Infectious Diseases Society of America has done the drilling for the health and infectious disease line items, and I'm sorry to say the news is not good.

Worst first: The proposed budget would cut funding for the CDC's antimicrobial resistance programs by 50%, $8.6 million. That means that only 20 state or local health departments, or health care institutions, will get money from CDC for surveillance and control of resistant bugs. That's only 40% of what was funded this year, when 48 health departments and health systems were funded. Which is very disturbing: If there's one thing almost everyone agrees on with regard to MRSA, it's that we need moresurveillance, not less.

In addition, all state grants in the Get Smart About Antibiotics program, which runs campaigns to reduce inappropriate use, get zeroed out.

There are other cuts as well to infectious-disease program at CDC and elsewhere in HHS, including to to a major childhood immunization program and to pandemic defenses. And funding for HIV/AIDS, TB and other NIH research programs barely tiptoe upward.But these frank cuts in programs to combat antimicrobial resistance, at a time when MRSA is burgeoning, Gram negative organisms such as Acinetobacter are gaining ground, and drug development is stalling, surely cannot be smart.

The IDSA analyis is here.

29 DECEMBER 2009

Another resistant bug rising: Acinetobacter

From the excellent and forward-thinking research team at Extending the Cure comes a dismaying report: over 7 years, a more than 3-fold increase in resistance in the Gram-negative bacterium Acinetobacter baumanii to its drug of last resort, imipenem.

Because MRSA is a Gram-positive, we don't talk much here about the Gram-negatives — the two categories of bacteria have different cell-wall structures and thus are treated using different categories of drugs. (That structural difference causes them to react in different ways to a stain invented by a scientist named Gram in the 19th century.) But the resistance situation with Gram-negatives is at least as dire as with MRSA, possible more so, because there are fewer new drugs for Gram-negatives in the pharmacology pipeline (as discussed in a New Yorker article by Dr. Jerome Groopman last year.)

And Acinetobacter is one nasty bug, as science journalist Steve Silberman ably documented in Wired in 2007 when he traced the spread of the organism through the military medical-evacuation chain from Iraq, demonstrating that the vast increase in resistant Acinetobacter among US forces was due to our own poor infection control.

The Extending the Cure paper (which will be published in February in Infection Control and Hospital Epidemiology) puts hard numbers to the Acinetobacter problem. Drawing on data from the private Surveillance Network, which gathers real-time electronic results from 300 US hospitals, they find:
  • full resistance to imipenem rose from 4.5% of isolates in 1999 to 18.2% in 2006 — a 300% increase
  • intermediate resistance rose from 1.3% of isolates to 9.4 — a 623% increase
  • susceptible isolates declined from 94.1% to 72.4% — a 23% decrease.
The authors write:
Our results demonstrate substantial national and regional increases in carbapenem resistance among clinical isolates of Acinetobacter species over the period 1999–2006. Increasing carbapenem resistance among Acinetobacter species is particularly troubling, because it is very often associated with multidrug resistance and because it is occurring in the context of increases in the incidence of Acinetobacter infection.

There's a further point to be made that is not explicit in the paper that I can see (though it is often made by Extending the Cure researchers). Acinetobacter needs attention, just as MRSA does — but if we focus just on the individual organisms, we are not going far enough. Antibiotic resistance is a system problem: It is an issue of infection control, of drug development, of agricultural organization, of federal priorities. It needs sustained attention and comprehensive, thoughtful, wide-ranging response. Now would not be too soon.

Monday, March 11, 2013

Rise of superbugs threatens antibiotic crisis

source: http://www.guardian.co.uk/society/2013/jan/24/antibiotics-mrsa


Rise of superbugs threatens antibiotic crisis


Lethal drug-resistant organisms mean threat must be listed on register of civil emergencies, says chief medical officer 
-    , science correspondent

'What is alarming is the rate at which bacteria are becoming resistant to antibiotics', says WHO adviser Dr Danilo Lo Fo Wong. Photograph: Murdo Macleod
An extraordinary scene plays out in hospitals across Britain that is a harbinger of crisis ahead. Patients brought in for routine operations pick up infections that until recent times seemed trivial. Now they can be killers. Even the most modern, and powerful, antibiotics can no longer save them.
The story of the superbug MRSA raised awareness of the growing uselessness of antibiotics, but that has been brought largely under control through better hygiene, at least in the UK.
The rise of other lethal drug-resistant organisms, including salmonella, TB, and E coli, continues, and the chief medical officer, Dame Sally Davies, warned MPs this week the threat must be listed on the government's National Register of Civil Emergencies.
The problem is not a local one. In Davos on Thursday, health officials gathered for a session called "The dangers of hubris to human health", after the World Economic Forum listed antibiotic resistance in its Global Risks report this month. The meeting's aim was to reassess the risks posed by the abuse and misuse of antibiotics that make lethal bacteria immune to our best defences. The meeting acknowledged that the historic success of antibiotics has lulled us into a false sense of security.
"To put it bluntly, we are running out of ideas. That's the problem we face. For many years we have been one step ahead of evolution, but in the past 25 years, we have failed to develop new antibiotics," said Danilo Lo Fo Wong, a senior adviser on antimicrobial resistance to the World Health Organisation.
The rise of antibiotic resistance began when they were introduced 60 years ago. Whenever the drugs are used, they wipe out weak bugs but survivors multiply and become ever more resilient the more antibiotics are used: natural selection in action.
"What is alarming is the rate at which bacteria are becoming resistant to antibiotics," says Dr Wong. "We are increasingly seeing infections that do not respond to these drugs, and the more treatments fail, the more people die."
Over the past 60 years, the pharmaceutical industry has churned out three generations of antibiotics. The first included natural penicillins. These fell by the wayside as bacteria evolved enzymes that broke the drugs apart. The second were synthetic penicillins, modified in the lab to resist the bugs' enzymes. Bugs gained resistance to these too. The third generation, carbapenems, are modified even more. In 2003, the first microbes arrived in Britain that are immune to them.
In evidence to the science select committee this week, Davies told MPs that the pipeline for new antibiotics had dried up, and that the market model for delivering new antibiotics was broken.
The reasons are many. In the 1990s and 2000s, big pharma largely gave up on antibiotics, which made merely hundreds of millions of dollars, in favour of blockbuster drugs that made billions. They focused on drugs for chronic diseases, such as heart disease. These patients take drugs for years, rather than days, so profits are likely to be higher. At the same time, many pharmaceutical firms closed their research centres.
There are other problems. Bacteria evolve at such a rate that any new antibiotic that is developed has only a short window in which it will work. Knowing this, and that governments are doing their utmost to keep antibiotic prescriptions to a minimum, are hardly incentives to invest in a decade of research to find a new drug.
Wong said moves were in train to develop new business models for whenever a new antibiotic is developed. The idea is radical. Instead of rushing to market, through government support, the drug would be held in reserve for emergencies.
David Brown – inventor of Viagra and chair of the Babraham research campus near Cambridge, which is home to 32 biotech firms – said big pharma companies should focus on manufacturing, running clinical trials, and marketing drugs. The new ideas for those drugs, he said, will come from biotech companies and universities. Brown knows the industry well. He worked at Glaxo Smithkline, Pfizer and latterly was head of drug discovery at Roche.
Brown has partnered with Sunil Shaunak, professor of infectious diseases at Imperial College London, to develop a radical new approach to combating bacterial infections, one that bugs cannot become resistant to. Instead of killing the bacteria, it manipulates the person's defences to prevent bugs getting into the bloodstream.
"Continuing with the old-fashioned approach of attacking bacteria is running out of steam. We need to re-educate people that antibiotics are not a panacea," said Shaunak. In early trials, the drug has proved "as good as you could ever imagine", added Brown.
One major hurdle faced by drugs companies is the regulatory hoops they must jump through to get a drug to market. Typically, a company must do two large-scale trials, involving thousands of people, before a drug is approved. "The problem is, if we wait until we can do two large-scale trials, we've waited too late. The epidemic is upon us," said John Rex, head of infection, global medicines development, at AstraZeneca.
A new strategy put forward by Rex and others is to be adopted by the European Medicines Agency and the Food and Drug Administration in the US. Under the new proposals, drug companies will do what trials they can in infected people, but can run more safety tests in healthy people, and prove efficacy through tests on bugs in laboratories. "This speeds the process up enormously, because for some drugs, the speed right now is zero."
Any antibiotics that are approved through the new regulations may be labelled to declare their limited testing, and be handed only to specialist doctors, to use only if they have no other options.
"Modern medicine is not possible without effective antibiotics and the global pipeline is frighteningly thin," he said. "If we don't fix this, we are all in serious trouble. It means not getting that hip replaced, not having care for your premature baby, and not having cancer treated."